


GLP-1RA Research: How Real-World Imaging Data Supports Evidence Generation Across Therapeutic Areas
Reading time /
7min
Industry

TL;DR
- GLP-1 receptor agonists are moving well beyond T2DM and weight management, with accumulating trial and real-world evidence pointing to applications in neurology, cardiology, oncology, nephrology, and metabolic liver disease.
- Claims data and EHRs surfaced many of those signals, but they can't supply structural and functional evidence. Imaging can: VAT/SAT from abdominal CT, liver fat via MRI-PDFF, beta-cell mass from GLP-1 receptor PET, hypothalamic activation from fMRI, and cardiac remodeling from cardiac MRI.
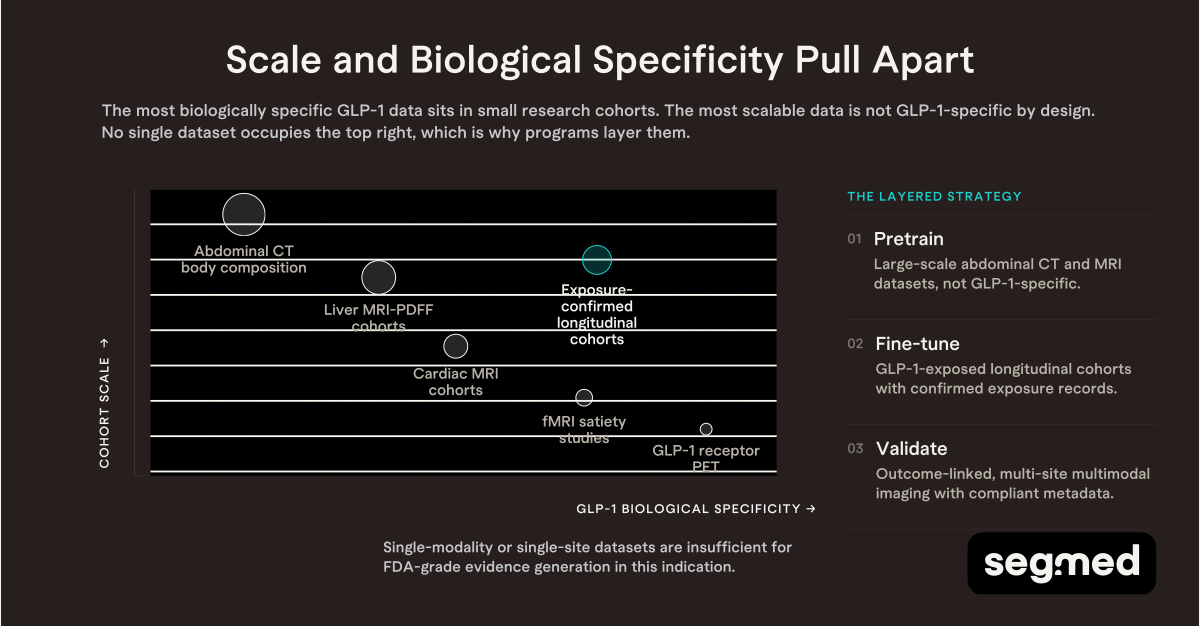
- There is no single standardized GLP-1 imaging dataset. The most biologically specific data (GLP-1 receptor PET) sits in small research cohorts; the most scalable data (abdominal CT, liver MRI) isn't GLP-1-specific by design.
- The practical path is a layered strategy matched to research objective large-scale imaging for pretraining, GLP-1-exposed longitudinal cohorts for fine-tuning, outcome-linked multimodal data for regulatory validation. Single-site or single-modality datasets won't carry FDA-grade evidence generation.
Introduction
Glucagon-like peptide-1 receptor agonists (GLP-1RAs) have established a documented clinical record beyond their original indication. Approved initially for Type 2 Diabetes Mellitus and metabolic disease, accumulating real-world and trial evidence is extending their relevance into neurology, cardiology, oncology, and nephrology. Real-World Data (RWD) has been instrumental in surfacing these new indications. Real-world imaging datasets, RWiD) add a further dimension. Structural and functional imaging evidence that neither claims data nor electronic health records alone can provide.
There is, however, no single standardized GLP-1 imaging dataset. GLP-1 is a physiological target, not an imaging label, and the data that exists is distributed across academic repositories, proprietary clinical trial archives, and real-world imaging networks (with significant variation in cohort size, modality, and access terms). The most biologically specific datasets (GLP-1 receptor PET imaging using tracers such as ⁶⁸Ga-NODAGA-Exendin-4) are typically small-cohort research studies, not machine learning-ready corpora. The most scalable datasets (abdominal CT body composition, liver MRI-PDFF, longitudinal metabolic imaging) are not GLP-1-specific by design but carry the imaging signal most relevant to drug response modeling. Navigating this landscape (and assembling data that is both scientifically valid and compliant for regulatory use) is the operational challenge GLP-1 researchers face at the outset of any imaging-based program.
Current Use Cases of GLP-1RAs
GLP-1RAs were initially approved for managing type 2 Diabetes Mellitus (T2DM). Clinical trials and real-world studies have since identified additional indications:
- Improved glycemic variability and reduction in diabetes-related complications
- Weight control and management
- Reduction in major adverse cardiovascular events
Expected and Emerging Use Cases
The therapeutic landscape of GLP-1RAs is shifting, with research identifying applications beyond metabolic health across neurology, cardiology, oncology, and other areas.
Neurology
Neuroprotective and neuro-regenerative effects of GLP-1RAs: Pre-clinical studies indicate that GLP-1RAs may carry neuroprotective activity. Observed effects include reduction of inflammation, promotion of neurogenesis, enhancement of neuron survival, improvement of synaptic function and plasticity, improvement of vascular function, and reduction of oxidative stress. These mechanisms suggest potential applications in slowing disease progression in Alzheimer's disease, Parkinson's disease, and other neurodegenerative disorders, as well as prevention and early recovery from stroke and slowing vision loss in glaucoma. Brain imaging , including fMRI of hypothalamic and reward circuits and PET of glucose metabolism, provides the structural and functional evidence base for tracking these effects in human populations.
Cardiology
Cardioprotective effects of GLP-1RAs: Advanced research has documented cardioprotective activity in diabetic populations. Ongoing early-stage research is examining whether these effects extend to non-diabetic patients. GLP-1RAs appear to improve endothelial function, modulate the renin-angiotensin system, and reduce cardiac tissue inflammation and scarring. Direct effects on heart tissue and blood vessels have been observed through mechanisms that are not yet fully characterized. Anti-atherogenic effects, plaque stabilization, reduced cardiac load, and improved cardiac activity have been reported. Cardiac MRI, including measurement of epicardial fat and structural cardiac remodeling, is a primary imaging modality for capturing these endpoints in longitudinal research.
Oncology
Cancer prevention and therapy: Early research and preclinical studies suggest GLP-1RAs may reduce the risk of certain cancers. The mechanism is not fully characterized, but effects on modulating insulin-like growth factors and reducing inflammation may contribute to cancer management. Some studies indicate potential apoptotic activity. Imaging data, including PET for metabolic activity and MRI for tumor burden, supports biomarker development in this indication.
Nephrology
Renal protective effects: Early studies indicate GLP-1RAs may benefit patients with chronic kidney disease (CKD), both by preventing and reducing kidney damage and thereby improving renal function. Current trials are focused on diabetic patients, but early research suggests potential efficacy in non-diabetic populations as well.
Other metabolic disorders
GLP-1RAs may play a role in diseases closely associated with diabetes and obesity, including non-alcoholic fatty liver disease (NAFLD), non-alcoholic steatohepatitis (NASH), and Polyendocrine Metabolic Ovarian Syndrome (PMOS). In NASH and NAFLD, GLP-1RAs have shown potential for reducing liver fat content and improving liver function, endpoints measurable via MRI proton density fat fraction (MRI-PDFF), which has become the validated imaging standard for liver fat quantification in interventional studies. In PMOS, they support management of insulin resistance.

RWD in GLP-1RA Research
RWD has become a foundational component of GLP-1RA research across all approved and emerging indications. Unlike traditional clinical trials, RWD provides insights from diverse patient populations and real-life clinical scenarios, capturing outcomes not observed under controlled lab conditions. RWD contributes to GLP-1RA research at multiple stages:
- Identifying new biomarkers that provide insights into early diagnosis, disease progression, and therapy response.
- Improving understanding of disease subtypes and progression through analysis of EHRs, claims data, and patient-reported outcomes across different population groups.
- Optimizing clinical trial design and execution by enabling identification of suitable endpoints and patient cohorts, thereby refining inclusion and exclusion criteria.
- Serving as an external control arm for trials.
- Supporting real-world evidence (RWE) generation on the efficacy and safety of interventions.
How RWiD enhances GLP-1RA Research
RWiD are an essential complement to traditional RWD sources such as EHRs and claims data. Imaging data provides structural and functional evidence that longitudinal clinical records cannot replicate, enabling more precise characterization of disease progression and drug response. By incorporating real-world imaging alongside clinical data, researchers can track disease progression, assess organ-specific effects of GLP-1RAs, and evaluate long-term therapeutic outcomes with greater accuracy.
- Biomarker Discovery: Advanced imaging modalities, including PET/CT, MRI, and abdominal CT, provide quantifiable, reproducible measures of disease processes and drug response that laboratory values cannot capture. In the GLP-1 context, the imaging biomarkers with the most validated research utility include: visceral adipose tissue (VAT) and subcutaneous adipose tissue (SAT) volume from abdominal CT; liver fat fraction (MRI-PDFF) for NAFLD and NASH endpoints; pancreatic beta-cell mass estimates from GLP-1 receptor PET; hypothalamic activation patterns from fMRI satiety studies; and cardiometabolic structural changes from cardiac MRI. Real-world imaging datasets that span these modalities, and link them to longitudinal clinical outcomes, enable discovery and validation of imaging biomarkers for predicting GLP-1RA response, tracking disease progression, and supporting regulatory evidence generation.
- Real-World Evidence and Post-Market Surveillance: Medical imaging datasets provide visual evidence of effectiveness, safety, and unexpected or unintended effects of GLP-1RAs across diverse patient populations and clinical settings.
- Clinical Trial Optimization: Analysis of RWiD provides evidence on imaging biomarkers, patient cohorts, endpoints, milestones, and interventions for the disease in focus. These insights support enhanced clinical trial design and improve efficiency and speed. Imaging data also supports patient stratification by identifying subgroups, improving the precision and relevance of trial results.
- Patient Stratification: RWiD can stratify patients based on imaging profiles, ensuring that GLP-1RAs are targeted to those most likely to benefit and that research findings are interpretable across clinically distinct subgroups.
- External Control Arm: Real-world imaging datasets, when integrated with other datasets function as external control arms. Detailed, longitudinal imaging records make trials more efficient and support ethical study design.
- Algorithm Development and Validation: When combined with AI and machine learning, real-world imaging datasets enable detection of subtle patterns and changes across large patient volumes. AI-powered analysis can automatically quantify changes in body composition, brain structure, amyloid burden, or liver fat providing standardized and scalable biomarkers for research and clinical application.
- Precision and Personalized Medicine: When RWiD is combined with other RWD types, it supports imaging biomarker discovery and patient stratification based on disease type and drug response, facilitating development of individualized care pathways.
Selecting the Right Imaging Data for Your GLP-1 Program
The imaging data appropriate for a GLP-1 research program depends on the research objective. The table below maps common GLP-1 research goals to the imaging data types and modalities that carry the most relevant signal:
In practice, the strongest GLP-1 imaging programs combine data layers: large-scale abdominal CT or MRI datasets for model pretraining, GLP-1-exposed longitudinal cohorts for fine-tuning, and outcome-linked multimodal data for regulatory validation. Single-modality or single-site datasets are insufficient for FDA-grade evidence generation in this indication. The most valuable GLP-1 imaging data is not held in public repositories, it resides within clinical trial archives, hospital imaging networks, and real-world care settings. Accessing it requires a data infrastructure that connects research demand to clinical supply at scale, with the compliance controls that regulatory use requires.
For programs that require a purpose-built starting point rather than a custom cohort assembly, the PRISM GLP-1 Longitudinal Imaging Biomarkers & Outcomes Cohort covers patients with confirmed exposure to semaglutide, tirzepatide, liraglutide, or dulaglutide, spanning 2017 to 2025 across DEXA, abdominal MR with PDFF and elastography, and CT. It delivers a broad set of imaging-derived biomarkers and is refreshed quarterly. Access is by inquiry.
How PRISM Compares to Commonly Used GLP-1 Imaging Datasets
No single public repository was designed with GLP-1 drug exposure as an organizing variable. The datasets most used in GLP-1 imaging research carry trade-offs between scale, biological specificity, and access terms. The table below summarizes the options researchers encounter most frequently.
The practical distinction for research design is between datasets that contain imaging relevant to GLP-1 biology and datasets that confirm GLP-1 drug exposure with linked longitudinal imaging. Large public repositories provide scale and modality breadth for pretraining and biomarker development. Purpose-built cohorts with verified drug exposure records (including baseline and follow-up scans, medication start and stop dates, dose information, and a matched comparator group) are required to establish treatment effects.
How Segmed Supports GLP-1RA Research
Segmed provides access to regulatory-grade real-world imaging datasets and associated clinical data drawn from a global network of healthcare provider partners spanning multiple continents and care settings. The depth and diversity of this network enables researchers to identify imaging cohorts relevant to specific GLP-1 therapeutic areas, whether the focus is liver fat quantification in NASH trials, body composition modeling for obesity drug response, cardiac structural changes in cardiovascular outcomes research, or brain imaging for neurodegenerative endpoints. Researchers can order access to the PRISM GLP-1 Longitudinal Imaging Biomarkers & Outcomes Cohort or request a custom dataset through our Concierge Service.
Specific research applications Segmed's datasets support include:
- Identifying imaging biomarkers for tracking disease progression or therapeutic outcomes in neurology, cardiology, and oncology.
- Accelerating clinical trials by offering providing pre-curated datasets for hypothesis generation and validation.
- Supporting patient stratification through integration with advanced analytics and machine learning pipelines.
- Generating real-world evidence for regulatory submissions and post-market surveillance.
- Assembling longitudinal, multi-site imaging cohorts that meet the diversity requirements of FDA review.
Segmed's medical and technical subject matter experts provide end-to-end curation support, ensuring datasets are structured and annotated to the requirements of specific research protocols. This includes de-identification through Incognito, Segmed's HIPAA Safe Harbor-compliant tool for DICOM and text report de-identification, and access through Openda, Segmed's imaging data platform, which supports modality-specific search, longitudinal patient-level navigation, and PET/CT and PET/MR data retrieval.
Data delivered through Segmed is compliant with SOC 2 Type II, HIPAA, and ISO 27001, the compliance baseline that regulatory submissions and institutional data governance require.
Conclusion
GLP-1RAs have an established record in diabetes and obesity management, and the documented evidence base for their application in neurology, cardiology, oncology, nephrology, and metabolic liver disease is growing. Real-world imaging datasets, are instrumental in this expansion, providing structural and functional evidence that characterizes drug response, supports patient stratification, and meets the evidentiary standards of regulatory review.
There is no single GLP-1 imaging dataset that serves all research goals. The practical path is a layered data strategy: matched to research objective, grounded in longitudinal clinical context, and built on imaging modalities (CT, MRI-PDFF, PET/CT, fMRI) that carry validated signal for the GLP-1 endpoints under investigation. Assembling that data at scale, with compliance and curation built in, is where research velocity is won or lost. For programmes that need a starting point rather than a custom build, Segmed's PRISM GLP-1 Longitudinal Imaging Biomarkers & Outcomes Cohort delivers exposure-confirmed longitudinal imaging,across DEXA, abdominal MR with PDFF and elastography, and CT, with a broad panel of imaging-derived biomarkers refreshed quarterly.
Connect with us to discuss how Segmed's datasets and curation capabilities align with your GLP-1 research goals, whether you are developing an AI model for body composition analysis, designing an external control arm for a GLP-1 trial, or generating real-world evidence for a regulatory submission.
Frequented Asked Questions - F.A.Q.
Are GLP-1 receptor agonists only used for diabetes and weight loss?
No. They were initially approved for Type 2 Diabetes Mellitus, with established indications now covering glycemic variability, weight management, and reduction in major adverse cardiovascular events. Accumulating trial and real-world evidence is extending their relevance into neurology, cardiology, oncology, nephrology, and metabolic liver disease.
Why are claims data and EHR data not enough for GLP-1 research?
Claims data and electronic health records surfacedsurfaced with many of the emerging GLP-1 signals, but they can't supply structural and functional evidence. Imaging can provide quantifiable metrics such as VAT/SAT from abdominal CT, liver fat via MRI-PDFF, beta-cell mass from GLP-1 receptor PET, hypothalamic activation from fMRI, and cardiac remodeling from cardiac MRI.
Is there a standardized GLP-1 imaging dataset?
No single standardized GLP-1 imaging dataset exists in the public domain. GLP-1 is a physiological target rather than an imaging label, so relevant data sits distributed across academic repositories, proprietary clinical trial archives, and real-world imaging networks, with wide variation in cohort size, modality, and access terms. Pre-built research cohorts are one route around that fragmentation: Segmed's PRISM GLP-1 Longitudinal Imaging Biomarkers & Outcomes Cohort covers patients with confirmed exposure to semaglutide, tirzepatide, liraglutide, or dulaglutide, spanning 2017 to 2025 across DEXA, abdominal MR with PDFF and elastography, and CT.
Why is GLP-1 imaging data hard to source?
The most biologically specific datasets (GLP-1 receptor PET using tracers such as ⁶⁸Ga-NODAGA-Exendin-4) are typically small-cohort research studies, not machine learning-ready corpora. The most scalable datasets, like abdominal CT body composition and liver MRI-PDFF, aren't GLP-1-specific by design but carry the signal most relevant to drug response modeling.
Which imaging biomarkers have the most validated utility in GLP-1 research?
Visceral and subcutaneous adipose tissue volume from abdominal CT; liver fat fraction (MRI-PDFF) for NAFLD and NASH endpoints; pancreatic beta-cell mass estimates from GLP-1 receptor PET; hypothalamic activation patterns from fMRI satiety studies; and cardiometabolic structural changes from cardiac MRI.
What imaging modality should I use for my research objective?
It depends on the goal. Drug response prediction relies on abdominal CT (VAT/SAT) and MRI-PDFF; mechanistic receptor biology on PET/CT with exendin-based tracers; CNS appetite regulation on fMRI and brain PET; regulatory-grade AI validation on multi-site, multi-modality CT, MRI, and PET/CT.
Can a single-site or single-modality imaging dataset support an FDA submission?
No. Single-modality or single-site datasets are insufficient for FDA-grade evidence generation in this indication. The workable approach is layered: large-scale imaging for pretraining, GLP-1-exposed longitudinal cohorts for fine-tuning, and outcome-linked multimodal data for regulatory validation.
How does imaging support clinical trial design in GLP-1 programs?
Real-world imaging data informs endpoint selection, cohort identification, and inclusion/exclusion criteria, and supports patient stratification by identifying clinically distinct subgroups. When integrated with other datasets, longitudinal imaging records can also function as an external control arm.
What compliance standards apply to imaging data used in regulatory submissions?
Data delivered through Segmed is compliant with SOC 2 Type II, HIPAA, and ISO 27001. De-identification runs through Incognito, Segmed's HIPAA Safe Harbor-compliant tool for DICOM and text report de-identification.